Spire Healthcare Accepts £1.03 Billion Takeover Amid NHS Backlogs
Spire Healthcare’s £1.03 billion takeover promises faster investment in hospitals and technology, but its impact will turn on debt, data governance and how the group balances private growth with NHS-funded care.


A Cash Deal After a Long Search
Spire Healthcare has accepted a £1.0265 billion cash takeover that would move Britain’s largest private hospital group off the London market and into the hands of an investor consortium. The September 5 offer from funds managed by Toscafund, Three Hills and Ares values each share at 250 pence. For health-data leaders, the transaction matters beyond ownership: the buyers are explicitly tying their case to technology, infrastructure and faster operational change across a nationally significant care network.
The price is 66.2% above Spire’s undisturbed market value on May 13, before the approach became public, and implies an enterprise value of about £2.31 billion. Reuters reported that holders of 53.4% of the stock had already committed to support the deal. Those commitments give the consortium a strong starting position, but they do not complete the acquisition; court, shareholder and regulatory conditions still stand between agreement and control.
Spire’s board did not arrive at the offer through a brief bilateral negotiation. The formal filing says advisers contacted 60 potential buyers during an eight-month strategic review. Earlier discussions with Bridgepoint and Triton ended without a deal, while the Toscafund-led group produced the only proposal the board considered deliverable and acceptable. That process supports the board’s claim that 250 pence was the best available cash outcome, even though the same price failed to win support in a separate 2021 bid.
The timetable now points to completion in the fourth quarter of 2026 or the first quarter of 2027. Until then, Spire remains a listed operator with its existing clinical responsibilities and disclosure duties. The distinction matters: a recommended scheme is not a finished sale, and investment promises are intentions rather than funded delivery plans. Technology teams should therefore treat the announcement as the start of a transition-risk period, not as evidence that capital programs have already accelerated.
Why the Board Chose Private Ownership
The takeover arrives after a financially resilient but operationally demanding year. Spire’s results show 2025 revenue of £1.58 billion, up 4.5%, and adjusted EBITDA of £268.6 million, up 3.3%. Yet operating profit fell 10.8% to £122.6 million and profit before tax fell 51.4% to £18.6 million. The gap between growth and bottom-line performance explains why efficiency, pricing and disciplined investment feature so heavily in the strategic narrative.
Employment taxes, minimum-wage increases, energy costs and the changing mix of insured, self-pay and NHS work have all constrained margins. In its May update, Spire said private-patient revenue was growing strongly and NHS activity was progressing as expected, but it still forecast 2026 adjusted EBITDA broadly in line with 2025. Flat earnings during a period of rising demand create pressure to improve utilization without allowing throughput targets to erode safety or patient experience.
The consortium argues that private ownership will give management longer planning horizons and greater freedom to move quickly. Its stated priorities include hospital investment, staff development, innovation and digital transformation. The board says the buyers intend to preserve clinical governance and hospital-level autonomy, continue serving as an NHS partner, and respect existing employment rights. Those statements establish useful commitments, but they remain broad; measurable capital, workforce and safety plans will be the real test after completion.
Financing also deserves close scrutiny. The offer documents describe multiple senior, subordinated and bridge facilities used to finance the purchase and refinance existing obligations. The headline commitments cannot simply be added and treated as permanent operating debt because they serve different purposes and may be replaced. Even so, interest, refinancing and property costs can compete with clinical systems for cash, making post-deal disclosure on leverage, capital expenditure and technology spending central to assessing the buyers’ long-term claim.
A Major Node in Britain’s Mixed Care System
Spire operates 38 hospitals and more than 55 clinics, works with roughly 8,800 consultants and treated more than 1.36 million patients and workplace clients in 2025. It is also the country’s largest private provider of hip and knee operations by volume. That scale means changes to scheduling, diagnostics, referral pathways or capacity allocation can affect more than private customers; they can influence how quickly NHS-funded patients move through elective care.
The backdrop remains severe. The British Medical Association’s analysis counted about 7.27 million elective pathways in England in June 2026, representing roughly 6.15 million people. About 2.48 million pathways had waited longer than 18 weeks and more than 106,000 had waited over a year. The median wait was 11.9 weeks, compared with 7.5 weeks before the pandemic in June 2019.
Independent providers are already embedded in the public response. The government says they delivered 6.15 million NHS-funded appointments, tests and operations in the year covered by its latest release, nearly 500,000 more than a year earlier. Patients who switch to a nearby provider can sometimes shorten waits by months. Capacity purchased from Spire is therefore part of the NHS access strategy, even though the hospitals remain privately owned.
That interdependence creates a genuine policy tension. More independent capacity can reduce queues and offer patient choice, while critics fear that public money, clinicians and diagnostic resources may be drawn toward shareholder or lender returns. Fresh coverage has already framed the acquisition through that debate. The most useful test is empirical: whether NHS-funded volumes, waiting-time gains, quality and total cost improve after the ownership change.
The Technology Promise Needs Specific Controls
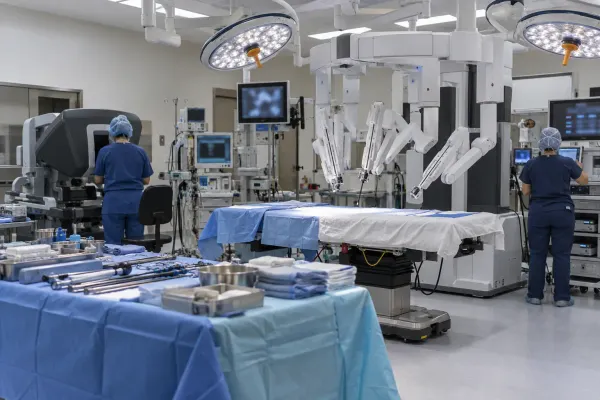
The buyers’ emphasis on technology is plausible because hospitals contain many investment bottlenecks: imaging equipment, theatres, pathology interfaces, booking platforms, electronic records, patient portals, cybersecurity and analytics. Spire has been centralizing administration in patient-support centers and pursuing a more digital patient journey. A private owner could approve upgrades faster, standardize systems across sites and use network-level data to match capacity with demand. Speed, however, is valuable only when clinical validation and local workflow design keep pace.
A transaction can also fragment accountability. Integration teams will need a precise inventory of applications, interfaces, devices, data processors and information-sharing agreements, including the boundary between Spire’s systems and NHS referral or reporting infrastructure. Changes in ownership do not reduce duties under UK data-protection law, medical-device rules or clinical-safety standards. Migration plans should preserve provenance, patient identity matching, retention schedules and audit trails while ensuring that cyber controls remain effective during organizational change.
Property strategy adds another layer. Twelve hospital assets were transferred in a 2026 sale-and-leaseback transaction financed for Blue Owl and Moor Park, according to the advisers’ confirmation. Leasing can release capital, but it separates ownership of buildings from operation of care. Future digital and clinical upgrades may therefore require coordination among Spire, its new owners and landlords, especially when work touches power, cooling, imaging suites, physical security or network infrastructure.
What Will Show Whether the Deal Delivers
The first indicators should be concrete rather than promotional. Stakeholders need to see annual capital expenditure, digital-program milestones, system availability, cybersecurity events, staff turnover, agency use and patient-experience measures alongside financial results. For NHS work, useful measures include referral-to-treatment time, cancellations, diagnostic turnaround, case mix and payments per completed pathway. Publishing the same definitions before and after the takeover would make it harder for ownership change to obscure deterioration or overstate improvement.
Clinical quality must remain the constraint on productivity. The offer cites strong inspection results, with 98% of inspected locations rated Good or Outstanding, or the equivalent, but historical ratings do not guarantee future performance. Boards should watch infection rates, readmissions, serious incidents, staffing ratios and complaints as activity changes. Digital automation should be evaluated for error, bias and override behavior, not only labor saved or appointments booked.
The acquisition is therefore neither a simple rescue nor proof of creeping privatization. It is a leveraged transfer of a large care network at a moment when public waiting lists make that network strategically important. If private ownership produces durable investment, reliable data exchange and more high-quality capacity, the effects could reach both insured patients and the NHS. If financing pressures dominate, the same scale could amplify risk. Completion conditions, published investment plans and consistent outcomes will decide which account proves accurate.