Europe Opens First Screening Week Amid Data Gaps
Europe’s first EU Screening Week makes blood pressure, cholesterol and glucose checks visible across the continent. Its harder test is whether health systems can connect abnormal results to equitable, measurable follow-up care.

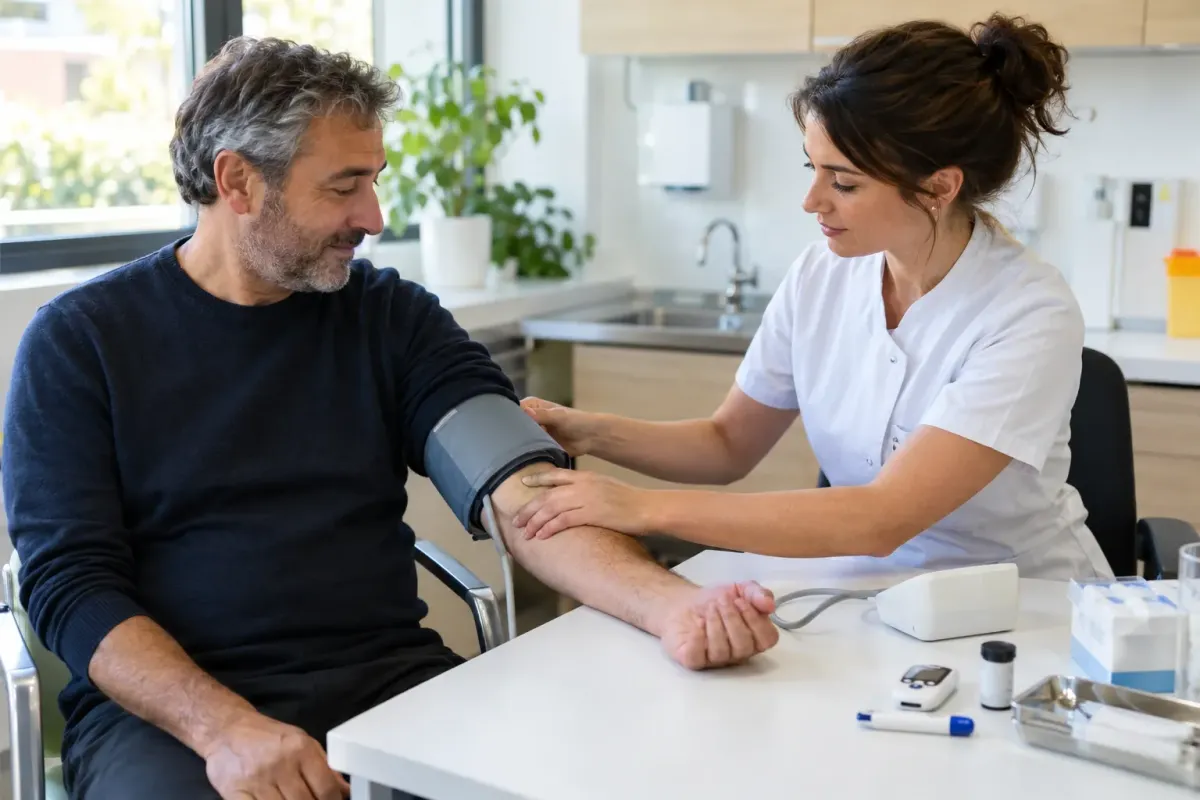
Europe’s first EU Screening Week opened Monday with a seven-day campaign built around three measurements: blood pressure, cholesterol and blood sugar. The campaign page frames those checks as an entry point to earlier action on cardiovascular and metabolic risk, but the initiative’s public-health value will depend less on how many tests are offered than on whether abnormal results lead to diagnosis, treatment and sustained follow-up.
The September 28–October 4 campaign is part of the European Commission’s “Know Your Numbers” effort and its broader Safe Hearts Plan. Free checks are being offered outside the Commission’s Berlaymont headquarters in Brussels, while national cardiology groups and partner organisations are running local activities. The country map shows how varied those projects are: Austria is using all nine federal provinces for community blood-pressure and rhythm checks among people 65 and older; Bulgaria is adding a risk-assessment tool to its national e-health application; Czech organisers plan stops in at least eight cities; and Finland is targeting adults aged 40 to 55 through pharmacies and local heart associations.
That diversity is useful because it puts prevention in places people already use. It also creates a natural policy experiment. A pharmacy station, a mobile event and an app can reach different populations, collect different data and produce very different referral patterns. Unless organisers use compatible definitions and track what happens after a positive result, the week may generate visibility without showing which delivery model actually closes a care gap.
A large burden hides behind simple measurements
The campaign focuses on factors that can remain silent for years. In the 27-member European Union, cardiovascular disease is associated with an estimated €282 billion in annual economic costs. The latest OECD review estimates that 22% of people in the EU live with hypertension, 15% with obesity and 8% with diabetes. It attributes more than three-quarters of cardiovascular deaths to modifiable risks, with metabolic factors such as high blood pressure, diabetes and obesity contributing the largest share.
The burden is not evenly distributed. Across the wider WHO European Region, cardiovascular disease accounts for 42.5% of deaths, and the burden is higher among men and in the eastern part of the region, according to WHO data. That geography matters for an EU-wide campaign. A common slogan does not erase differences in primary-care capacity, insurance coverage, laboratory access, medicine availability or trust in public institutions.
Even basic measurement is inconsistent. More than 30% of EU adults aged 45 to 54 had not had their blood pressure measured in the previous year, the OECD found, and about 6% had not had it measured in five years. More than 10% had gone at least five years without a cholesterol or blood-glucose test. Those figures support the case for easier access, but they do not reveal who was missed, why they were missed or whether a one-time public event can reach them.
The proposed health check goes beyond three numbers
Screening Week is an awareness campaign, not yet a uniform clinical program. The Commission’s Safe Hearts strategy, introduced in December 2025, calls for a more coordinated European approach to prevention, early detection and treatment. Scientific organisations have since proposed a structured cardiovascular-renal-metabolic check for all 27 member states.
The task-force proposal recommends at least one check for people younger than 35, systematic checks at least every five years from ages 35 to 65, and more frequent assessment later in life. Its proposed package is wider than the campaign’s three headline measurements. It includes lifestyle and family history; a full lipid profile; glucose and glycated haemoglobin; kidney function and urine albumin; body-mass index and waist measures; and, where appropriate, mental and reproductive health factors.
Those recommendations come from professional societies representing cardiovascular, kidney, diabetes and obesity specialists. They are not evidence that every element should be applied identically to every person or country. Local disease prevalence, age structure, existing primary-care coverage and the capacity to investigate abnormal results all affect the likely benefit. The proposal itself calls for adjustment to individual and local risk rather than a single unchanging interval.
A test is only the first step
Detecting an elevated value can be useful when an effective next step exists. Repeated blood-pressure measurement can confirm persistent hypertension; laboratory testing can distinguish transient glucose elevation from diabetes; and risk assessment can guide discussion of lifestyle support or medication. But a campaign measurement is not a diagnosis, and an abnormal result without a dependable handoff can add anxiety without reducing risk.
The evidence also cautions against equating broad health checks with better outcomes. A Cochrane review of general health checks found little or no effect on total, cardiovascular or cancer mortality, even though checks increased the detection of conditions such as hypertension and high cholesterol. The authors noted that many individual tests had been incompletely studied and that screening can increase diagnostic and therapeutic interventions. The studies largely evaluated older forms of broad checkups, so they do not settle the value of modern, targeted cardiometabolic programs; they do show why diagnosis counts alone are insufficient.
A WHO guide treats screening as an end-to-end pathway rather than a test. Programs need a defined target population, quality-assured measurement, confirmation, treatment capacity, informed participation and monitoring of benefits and harms. False positives can prompt avoidable tests, while false negatives can provide reassurance that delays care. Selective participation can also make a campaign appear successful while the people at highest risk remain under-represented.
Data infrastructure is the hidden intervention
For the week to inform policy, organisers need more than a total number screened. A minimum dataset would record the denominator of people invited, participant age and sex, broad socioeconomic or geographic indicators, measurement method, abnormal-result thresholds, confirmatory testing, completed referral and treatment initiation. Reporting should protect privacy and avoid turning a public event into an uncontrolled research database, but aggregate results must be comparable enough to identify who was reached and who was missed.
Digital tools can help with invitations, risk calculation, reminders and referral, but they can also reproduce exclusions. Bulgaria’s use of a national e-health application may scale quickly among insured users with digital access; it may be less useful for people without smartphones, stable coverage or digital confidence. Austria’s anonymous data collection could show participation patterns, but anonymity may limit linkage to later outcomes. These are not reasons to reject either model. They are design choices that determine what can be learned.
The EU already has a large implementation vehicle in the JACARDI program, a joint action involving 21 countries and more than 140 pilot projects on cardiovascular disease and diabetes. Its value to Screening Week is the possibility of testing shared indicators, evaluating outreach and transferring workable models between health systems. The essential comparison is not app versus pharmacy or mobile unit versus clinic; it is which combination reliably identifies risk and completes care for populations that routine services underserve.
What success should look like
The first EU Screening Week can reasonably be judged in stages. Immediate measures include participation, the share of first-time or overdue attendees, valid-test rates and the proportion receiving understandable results. Within weeks, organisers should know how many abnormal findings were confirmed and how many people completed a referral. Longer-term evaluation should examine treatment uptake, risk-factor control, repeat attendance, adverse consequences and whether gaps narrowed across income, education, sex, age and geography.
These outcomes are harder to communicate than a tally of free checks, but they distinguish public-health infrastructure from a publicity campaign. Europe’s cardiometabolic burden justifies action, and a visible week can normalize preventive conversations. The decisive question is whether the continent can connect a simple measurement to an equitable care pathway—and produce data strong enough to show that the connection worked.