Patients Want Clinicians Involved as Healthcare AI Expands
A new HIMSS survey finds 73% of patients welcome healthcare AI when a clinician remains involved, sharpening the case for visible oversight, accountable workflows and patient choice as U.S. adoption accelerates.


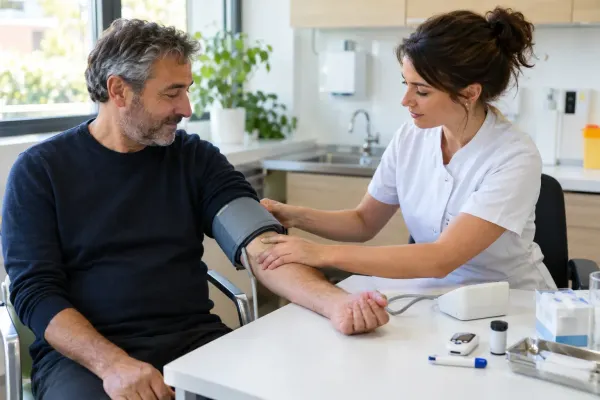
Healthcare artificial intelligence has crossed an important threshold: patients increasingly expect to encounter it, but they do not want it operating beyond recognizable human responsibility. A new HIMSS study of 1,500 people found that 73% were open to AI when a doctor or other healthcare professional remained involved. The finding is timely for North American health systems moving AI from experiments into documentation, imaging, decision support, patient messaging and administrative work.
The survey, released September 4, included 500 respondents in North America and equal groups in EMEA and Asia-Pacific. Two in three respondents reported at least some familiarity with healthcare AI, while 63% believed it was probably already used somewhere in their care. That means awareness is no longer the central barrier. The harder task is designing data practices, clinical workflows and accountability that patients can see and understand.
The report does not endorse blanket acceptance. Comfort reached 70% for the most support-oriented tasks but fell to 47% when AI suggested diagnoses or recommended treatments. North American and EMEA respondents leaned more heavily than Asia-Pacific respondents on human-in-the-loop oversight. The practical signal is that adoption should be sequenced by risk: convenience tools may earn consent faster, while clinical applications require stronger evidence, disclosure and review.
Comfort Falls as AI Approaches Clinical Judgment
Respondents most often believed providers already used AI for scheduling and reminders, cited by 52%, followed by reviewing test results at 48% and chatbots at 45%. Perceived use was lower for more consequential functions: 35% mentioned personalized recommendations or care plans and 33% said support for clinicians' decisions. These answers measure belief, not verified deployment, but they reveal where patients currently locate AI inside the care journey.
Comfort followed a similar gradient. Sixty-three percent were comfortable with AI recording or transcribing a visit, compared with 57% for detecting health issues earlier and 47% for suggesting possible diagnoses. The report page frames the divide as a choice between AI that supports human care and AI that appears to replace judgment. Hospitals should not interpret enthusiasm for transcription as permission to expand silently into treatment recommendations.
Patient preferences were also heterogeneous. Familiarity was 77% among respondents ages 18 to 34 but 53% among those 55 and older; urban familiarity was 72%, compared with 55% outside urban areas. Those gaps matter in the Americas, where digital access, health literacy and trust vary sharply across communities. A single disclosure or portal design will not serve every patient, especially when language, disability, connectivity or caregiver involvement changes how information is received.
Adoption Is Moving Faster Than a Shared Social Contract
Clinicians are already far along the adoption curve. An AMA survey released in March found that 81% of physicians used AI in practice, more than twice the 38% reported in 2023. More than three-quarters said AI improved their ability to care for patients. That professional confidence creates momentum, yet the HIMSS results show that patient acceptance depends on where the tool sits and who remains answerable for its output.
Patients are using general-purpose systems outside clinical channels as well. A Gallup poll for West Health reported in April that one in four U.S. adults had used AI tools or chatbots for physical or mental health information or advice, representing more than 66 million people. Provider governance cannot stop at purchased hospital software; care teams also need a safe way to discuss AI-generated information that patients bring into the encounter.
The contrast is not simply patients versus technology. Sixty-nine percent of HIMSS respondents were open to AI if a clinician stayed involved, 65% believed it could help clinicians make more accurate decisions and 59% said they would likely use provider-offered AI tools. Only 53% were open to autonomous AI for some healthcare tasks. The opportunity is substantial, but the acceptable product is a supervised service with defined limits, not an unaccountable substitute for care.
Ambient Scribes Show Both the Opportunity and Obligation
Ambient documentation illustrates why the distinction matters. A JAMA study of 263 clinicians across six health systems found burnout fell from 51.9% to 38.8% after 30 days with an ambient AI scribe, alongside improvements in after-hours documentation and attention to patients. The design was a quality-improvement study rather than a randomized trial, so it supports operational promise without proving that every product or setting will reproduce the result.
The patient-trust study found 63% comfortable with AI recording or transcribing visits, one of its clearest high-acceptance clinical uses. Still, recording creates distinct obligations around notice, consent, retention, access and correction. A generated note can become part of the legal medical record and influence later care. The clinician must review it for omissions, attribution errors and invented details before signing, while the organization must make correction paths clear to patients and staff.
That review cannot be ceremonial. HIMSS found clinician review was the top trust driver, selected by 46%, ahead of data protection and external oversight, each at 42%, and accountability at 40%. Respondents worried more about missing accountability and reduced human involvement, both at 89%, than about understanding the technology itself, at 76%. Patients are asking less for a technical lecture than for confidence that a qualified person is watching and will act when the system is wrong.
Federal Rules Cover Parts of a Larger Governance Problem
U.S. policy provides pieces of that assurance but not one comprehensive healthcare AI regime. The federal HTI-1 rule established transparency requirements for predictive decision-support interventions in certified health IT, a category that supports more than 96% of hospitals and 78% of office-based physicians. Developers must expose information that helps customers judge whether covered models are fair, appropriate, valid, effective and safe, yet many administrative and consumer-facing tools sit outside that exact certification pathway.
Medical-device oversight covers another slice. The FDA's updated device list identifies AI-enabled products authorized for U.S. marketing and links to public safety and effectiveness summaries, while cautioning that the list is not comprehensive. Joint principles from U.S., Canadian and British regulators emphasize performance of the human-AI team and clear, essential information for users. Neither mechanism replaces local validation after deployment.
The National Academy of Medicine has therefore made patient safety a system-level project, not only a product review. Its two-year initiative is developing a national strategy for using AI to prevent harm across U.S. care delivery. That work reflects the governance gap hospitals face now: a tool may be lawful to purchase and still be poorly integrated, weakly monitored, confusing to patients or unsafe for a population unlike the one on which it was evaluated.
Trust Must Become a Measurable Operating Requirement
Healthcare organizations can translate the survey into a concrete deployment sequence. Begin with a written intended use, the patient problem being solved and a named clinical owner. Record the model version, data inputs, excluded uses and evidence base. The voluntary NIST framework offers a useful structure to govern, map, measure and manage risk. Validate performance locally before broad rollout, then monitor accuracy, overrides, complaints, disparities and workflow burden. Higher-consequence systems should require tighter thresholds, clearer escalation and more frequent review than scheduling or billing automation.
Patient communication should be equally operational. Notice must say where AI is used, what it does, what information it processes, whether a clinician reviews the output and how a patient can question or correct the result. Consent should not be bundled into dense privacy language when audio is recorded or sensitive data are repurposed. Organizations also need alternatives for patients who decline, because a choice that makes timely care impractical is not meaningful choice.
The HIMSS findings are encouraging precisely because they are conditional. Patients are not rejecting healthcare AI; most can see value when technology strengthens a relationship they already trust. The durable path in the Americas is therefore visible supervision, accountable data use and evidence that the human-AI team performs better for the people actually served. Systems that treat those conditions as measurable requirements can scale responsibly. Those that treat trust as messaging may discover that adoption moves faster than legitimacy.